A proper laryngeal mask airway (LMA) seal supports effective ventilation while reducing unnecessary airway pressure and gas leakage. In 2026, clinicians still rely on careful patient assessment, device selection, and continuous monitoring. The question is practical: How to ensure a proper seal with a laryngeal mask airway when anatomy, positioning, and device design vary?
A reliable seal begins before insertion. Review the manufacturer’s instructions, select the correct size, and inspect the cuff for visible damage. Lubricate the posterior surface lightly, keeping lubricant away from the airway opening. After insertion, confirm resistance, chest movement, expired carbon dioxide, and bilateral breath sounds. A stable waveform matters more than a single reassuring sign.
Cuff inflation requires restraint. Overinflation can increase mucosal pressure and may worsen postoperative throat discomfort. Underinflation can produce an audible leak and inadequate ventilation. Use a cuff pressure manometer when available, rather than relying on finger feel. Small adjustments often work better than repeated reinsertion.
Positioning deserves attention. Head and neck alignment, jaw relaxation, and surgical movement can change the seal after placement. Recheck the airway after repositioning, connection changes, or altered ventilation settings. A quiet circuit is useful, but it is not proof of perfect placement.
Not every leak reflects poor technique. Patient anatomy, airway obstruction, obesity, and device limitations can contribute. Reflect honestly. If ventilation remains inadequate, follow local protocols and seek skilled assistance promptly. This overview supports clinical reasoning, but supervised training, institutional guidance, and current evidence remain essential for safe airway management.
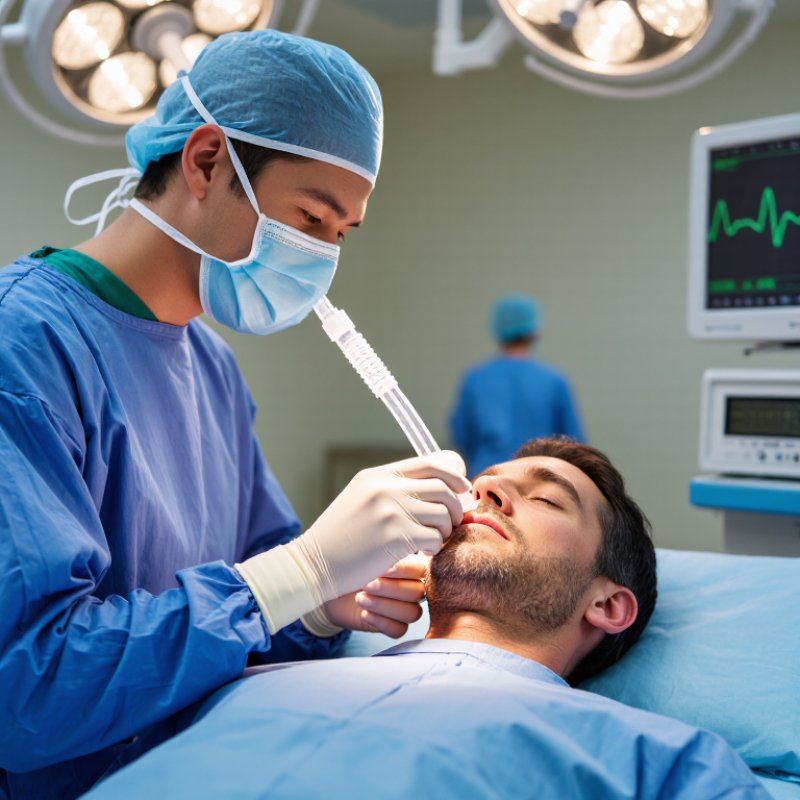
How to Ensure a Proper Laryngeal Mask Airway Seal in 2026?
Understanding Laryngeal Mask Airway Seal Principles
A proper laryngeal mask airway seal begins with anatomy, not force. The cuff should rest around the laryngeal inlet without folding or twisting. Seal quality depends on correct size, position, cuff pressure, and patient anatomy. In practice, even an experienced clinician can misjudge placement. Small errors matter.
After insertion, observe chest movement, tidal volume, airway pressure, and the capnography waveform. Listen for an audible leak around the mouth. Use a manometer when available, rather than judging pressure by pilot balloon firmness. The lowest cuff pressure that supports effective ventilation is usually preferable. Excessive pressure may injure surrounding tissues, while insufficient pressure can permit leakage or aspiration risk.
If ventilation remains difficult, reassess head and neck alignment, depth of insertion, and tube connections. A folded epiglottis or displaced mask may create a misleading seal. Gastric insufflation also deserves attention, especially when airway pressures rise. Device instructions should guide size selection and pressure limits, because designs differ. Patient factors, including obesity, restricted movement, airway abnormalities, and changing anesthetic depth, can alter the seal during care. I still find that rushed reassessment causes avoidable problems. A stable waveform can create false confidence, so the seal should be checked again after repositioning, surgical movement, or pressure changes.
Understanding Laryngeal Mask Airway Seal Principles
Commonly cited clinical reference ranges suggest keeping intracuff pressure around 40–60 cmH₂O and confirming an oropharyngeal leak pressure of at least 20 cmH₂O, with approximately 20–25 cmH₂O often used as a practical reference range. Actual targets vary by airway device, patient factors, ventilation requirements, and local protocol. Measure cuff pressure and confirm adequate ventilation rather than relying on volume alone.
How to Ensure a Proper Laryngeal Mask Airway Seal in 2026?
Selecting the Appropriate Laryngeal Mask Airway
Choosing the correct laryngeal mask airway starts with the patient, not the device drawer. Consider weight, age, airway anatomy, surgical position, and the planned ventilation pressure. A size chart provides direction, but it is not infallible. A broad tongue, limited mouth opening, or altered pharyngeal anatomy may require a different choice. Check the manufacturer’s sizing guidance and follow local clinical protocols.
The cuff should sit gently around the laryngeal inlet. Advance it without force, then inflate with the minimum volume needed for an effective seal. Use a cuff pressure manometer whenever possible. Excessive pressure can injure mucosa, while insufficient pressure may cause an audible leak or poor ventilation. Listen near the mouth. Observe chest movement, airway pressure, expired volume, and capnography. Small changes matter.
Patient positioning can alter the seal. Reassess after head movement, surgical repositioning, or changes in ventilation settings. A device that sealed well initially may leak later. This is easy to overlook. If ventilation remains inadequate, do not keep adding air automatically. Check depth, obstruction, gastric insufflation, and airway alignment. Reconsider the size or device type when appropriate. Clinical judgment improves with experience, yet no selection method works perfectly for every airway. When aspiration risk is high or ventilation demands are substantial, an alternative airway strategy may be more suitable.
Before insertion, assess more than mouth opening and Mallampati grade. Review fasting status, reflux symptoms, obesity, pregnancy, airway surgery, and aspiration risk. The 2022 American Society of Anesthesiologists difficult-airway guidance supports a documented airway plan, continuous oxygenation, and capnography when confirming ventilation. Prepare suction, a backup airway, alternative ventilation equipment, and functioning monitoring before induction. Small omissions matter.
Inspect the laryngeal mask airway for damage, then inflate and deflate the cuff to check symmetry. Apply a thin layer of water-soluble lubricant to the posterior surface, avoiding excess lubricant near the airway opening. Select the size according to the manufacturer’s weight range and the patient’s anatomy. Preoxygenate until oxygen reserve is adequate, position the head and neck carefully, and remove dentures only when they interfere. Keep the patient’s jaw relaxed; forceful insertion can fold the cuff.
After placement, confirm chest movement, a square capnogram, and stable oxygen saturation. Assess for an audible leak and measure cuff pressure when equipment is available; many clinical protocols aim to keep intracuff pressure below 60 cmH2O. The NAP4 report recorded 133 major airway complications and stressed planning, equipment readiness, and early recognition of failure. A perfect seal is not guaranteed. I still recheck positioning after surgical movement, because a previously quiet leak can appear suddenly.
How to Ensure a Proper Laryngeal Mask Airway Seal in 2026?
An effective seal begins before insertion. Choose a size that matches the patient’s weight, anatomy, and clinical need. Check the cuff for damage, then fully deflate it so the leading edge remains flat. Apply a thin layer of water-soluble lubricant to the posterior surface. Too much gel can obstruct the aperture. It can also become a distraction.
With the patient’s head gently extended and neck slightly flexed, open the mouth and guide the airway along the hard palate. Keep the tip moving posteriorly, not upward. Advance until resistance is felt in the hypopharynx, then inflate the cuff gradually. Avoid forcing the device. A 2022 Difficult Airway Society update supports limiting repeated attempts and reassessing ventilation early. That practical discipline protects patients when positioning is uncertain.
Confirm placement through chest movement, bilateral breath sounds, and a sustained capnography waveform. Check for leaks during gentle positive-pressure ventilation. A manometer is safer than estimating cuff pressure by touch; many clinical recommendations keep pressure below 60 cmH2O, while device instructions may differ. The NAP4 national airway audit documented serious complications involving supraglottic airways, including obstruction and aspiration. Depth markings alone are not proof of a seal. I have seen a seemingly clean waveform deteriorate after head movement. Recheck after repositioning, surgical preparation, or changing ventilation pressure. The first placement may look acceptable, yet still deserve another careful assessment.
How to Ensure a Proper Laryngeal Mask Airway Seal in 2026?
A reliable laryngeal mask airway seal begins with patient assessment, not cuff inflation. Check mouth opening, airway anatomy, aspiration risk, and surgical position. After insertion, confirm a square-wave capnogram, visible chest movement, and stable oxygenation. The 2022 American Society of Anesthesiologists Practice Guidelines support continuous exhaled-carbon-dioxide monitoring during general anesthesia. A seal is not proven by chest movement alone.
Measure cuff pressure with a manometer. Do not rely on finger feel. Many clinical protocols target pressures below 60 cmH2O, while ventilation should remain effective with the lowest pressure possible. Listen for an audible leak near the mouth, watch airway pressure trends, and reassess after head or neck movement. A 2023 systematic review in Anaesthesia reported first-attempt supraglottic airway success commonly above 90%, but success does not guarantee a stable seal. That distinction deserves more attention.
Tips: Use small air increments. Pause between adjustments. Recheck after repositioning, increased peak pressure, or surgical stimulation. Document cuff pressure, leak observations, ventilation settings, and capnography. In practice, I sometimes reassessed too late after table movement. That was a preventable gap. The 2024 Difficult Airway Society guidance continues to emphasize oxygenation, confirmation, and early escalation when ventilation becomes unreliable. Persistent leakage, gastric insufflation, or rising airway pressure should prompt structured troubleshooting, not repeated blind inflation.
| Assessment Dimension | What to Assess | Practical Reference | If the Seal Is Inadequate | Monitoring Frequency |
|---|---|---|---|---|
| Insertion and Position | Confirm easy ventilation, visible chest movement, bilateral breath sounds, and absence of significant obstruction. | Verify placement using clinical assessment and a continuous waveform capnogram after ventilation is established. | Stop and reassess head and neck position, insertion depth, cuff inflation, and possible malposition; replace the device if ventilation remains unreliable. | Immediately after insertion, after repositioning, and whenever ventilation changes. |
| Cuff Pressure | Measure intracuff pressure with a calibrated cuff manometer rather than estimating by palpation or syringe volume. | Use the lowest pressure that provides an effective seal and remain within the device-specific limit; many commonly used supraglottic airways specify a maximum of approximately 60 cmH2O. | If pressure is high, remove excess air in small increments while checking ventilation. If pressure is low with a leak, add only the minimum air needed. | After inflation, after major changes in airway pressure or temperature, and periodically during prolonged use. |
| Audible Leak | Listen around the mouth and neck during positive-pressure ventilation and observe for loss of delivered volume or visible gas escape. | A small leak may be acceptable if oxygenation, ventilation, and airway pressures remain satisfactory; a progressive or pronounced leak requires correction. | Check depth, alignment, cuff pressure, circuit connections, and peak airway pressure before deciding to reposition or exchange the device. | Continuously by clinical observation, with reassessment after every adjustment. |
| Oropharyngeal Leak Pressure | Assess the airway pressure at which an audible leak first occurs using a consistent, locally approved technique. | The seal pressure should exceed the pressure required for ventilation. Interpret the result with the clinical context rather than using one universal cutoff. | Reduce excessive inspiratory pressure where clinically possible, optimize positioning and cuff pressure, and consider a different airway strategy if an adequate seal cannot be achieved. | After placement when clinically useful, after troubleshooting, and when ventilation requirements increase. |
| Ventilation Performance | Review tidal volume, minute ventilation, peak airway pressure, compliance, and the difference between inspired and expired volume when available. | Use a consistent trend rather than a single reading. Falling expired volume or increasing pressure may indicate leak, obstruction, bronchospasm, or changing respiratory mechanics. | Check the patient, circuit, airway position, cuff pressure, and ventilator settings in a structured sequence. | Continuously during mechanical ventilation and after any clinical or ventilator change. |
| Gas Exchange | Monitor oxygen saturation, waveform capnography, end-tidal carbon dioxide trends, respiratory pattern, and clinical signs of inadequate ventilation. | A sustained capnogram and stable gas-exchange trends support effective airway function but do not, by themselves, exclude tissue pressure injury. | Immediately assess airway patency, displacement, circuit integrity, ventilation settings, and patient physiology; escalate if abnormalities persist. | Continuously while the airway is in use. |
| Hemodynamic and Tissue Effects | Observe for blood on removal, tongue or lip swelling, sore throat, dysphonia, difficulty swallowing, and signs of excessive cuff pressure. | Use the lowest effective cuff pressure and avoid repeated inflation beyond the device instructions. Document any trauma or postoperative airway symptoms. | Correct cuff pressure, reassess device position, and provide clinical follow-up when symptoms are persistent, severe, or associated with airway compromise. | During use, at removal, and during post-anesthesia recovery. |
| Documentation and Escalation | Record device size, insertion attempts, cuff pressure, leak assessment, ventilation parameters, capnography, and corrective actions. | Use a standardized airway checklist and follow local protocols, current device instructions, and the clinician’s assessment. | Escalate early when oxygenation or ventilation cannot be maintained, the airway repeatedly dislodges, aspiration is suspected, or an effective seal cannot be obtained. | At insertion, after interventions, during handover, and at removal. |
Clinical reference note: Cuff-pressure limits, measurement methods, and ventilation recommendations vary by supraglottic airway design. Always follow the instructions for use of the specific device and local airway-management protocols.
Consider weight, age, airway anatomy, surgical position, and planned ventilation pressure. Use sizing guidance, but do not treat it as infallible.
Inspect the cuff for damage. Fully deflate it until the leading edge lies flat. Apply a thin layer of water-soluble lubricant to the posterior surface.
Gently extend the head and slightly flex the neck. Guide the device along the hard palate, moving posteriorly. Never force it.
Inflate gradually with the minimum volume creating an effective seal. A cuff pressure manometer is preferable to judging pressure by touch.
Many clinical recommendations suggest keeping pressure below 60 cmH₂O. Always follow device instructions and local protocols.
Look for chest movement, bilateral breath sounds, expired volume, airway pressure, and a sustained capnography waveform. Depth markings alone are not proof.
Check insertion depth, airway obstruction, alignment, and gastric insufflation. Do not automatically add more air. Reconsider size or device type when needed.
Yes. Reassess after head movement, surgical repositioning, or ventilation changes. A seal can deteriorate later. Small changes matter.
Consider an alternative when aspiration risk is high or ventilation demands are substantial. No selection method works perfectly for every airway.
Ensuring a reliable laryngeal mask airway seal in 2026 depends on a structured approach that combines sound principles, suitable device selection, careful preparation, and continuous assessment. The clinician should understand how cuff design, airway anatomy, ventilation pressure, and tissue contact influence sealing performance. Choosing the appropriate size and type of airway according to the patient’s age, anatomy, procedure, and ventilation needs is essential. Before insertion, confirm that the equipment is intact, available, and correctly prepared, while positioning the patient to support safe airway access.
To understand how to ensure a proper seal with a laryngeal mask airway, insert the device gently along the natural curve of the palate and position it without excessive force. Confirm effective ventilation through chest movement, breath sounds, exhaled carbon dioxide, and the absence of significant air leakage. If the seal is inadequate, reassess depth, head and neck position, cuff condition, and ventilation settings before making controlled adjustments. Continuous monitoring is important because seal quality can change during anesthesia, repositioning, or pressure variations.

Mainline Medical